
Healthcare IoT and
connected care
platforms
Connectivity, ingestion, alerting and dashboards for connected medical devices.
The device is rarely the hard part
Connected care fails between the device and the care team, not at either end. Formats that need mapping, a gateway that drops out unnoticed, alerts nobody reads. All solvable, and all decided before the first device is connected.
What we build
Device connectivity
Connections over BLE, Wi-Fi, cellular and gateway hardware, including devices that were not designed to be connected to anything.
Data ingestion
Services that receive device data reliably at volume, handle retries and duplicates, and cope with devices that return with a backlog.
Normalisation and mapping
Readings from different manufacturers converted into a consistent structure, with units, timestamps and patient identity handled correctly.
Edge processing
Filtering, aggregation and initial checks on the device or gateway, for settings where bandwidth is limited or latency matters.
Alerting
Threshold and trend-based alerts, with severity, routing, acknowledgement and escalation designed around who is actually on duty.
Dashboards
Views for clinicians, care coordinators and operations teams, each showing what that role needs rather than everything the system holds.
Fleet management
Device registration, configuration, firmware status, connectivity health and battery state across a whole estate.
Clinical integration
Sending device data into EHR and clinical systems using FHIR or HL7 so that it appears where clinicians already work.
Device analytics
Usage, adherence, reliability and failure patterns across devices and cohorts.
Connected care in the field
Device consoles, dashboards and, where a client permits it, the hardware itself.
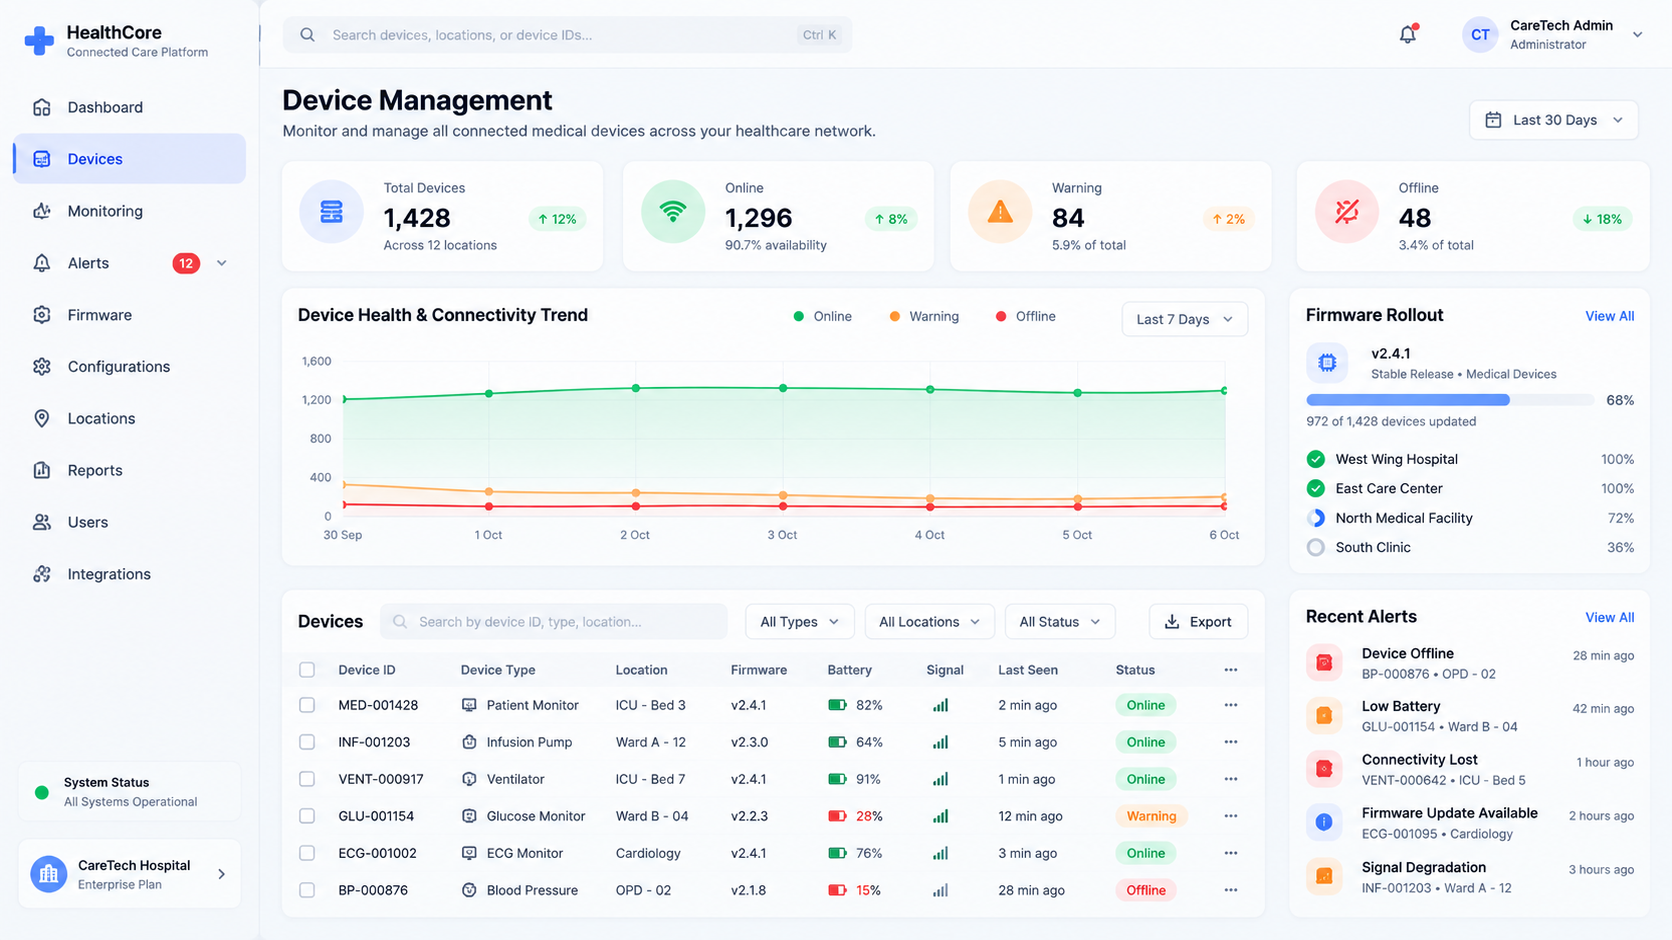
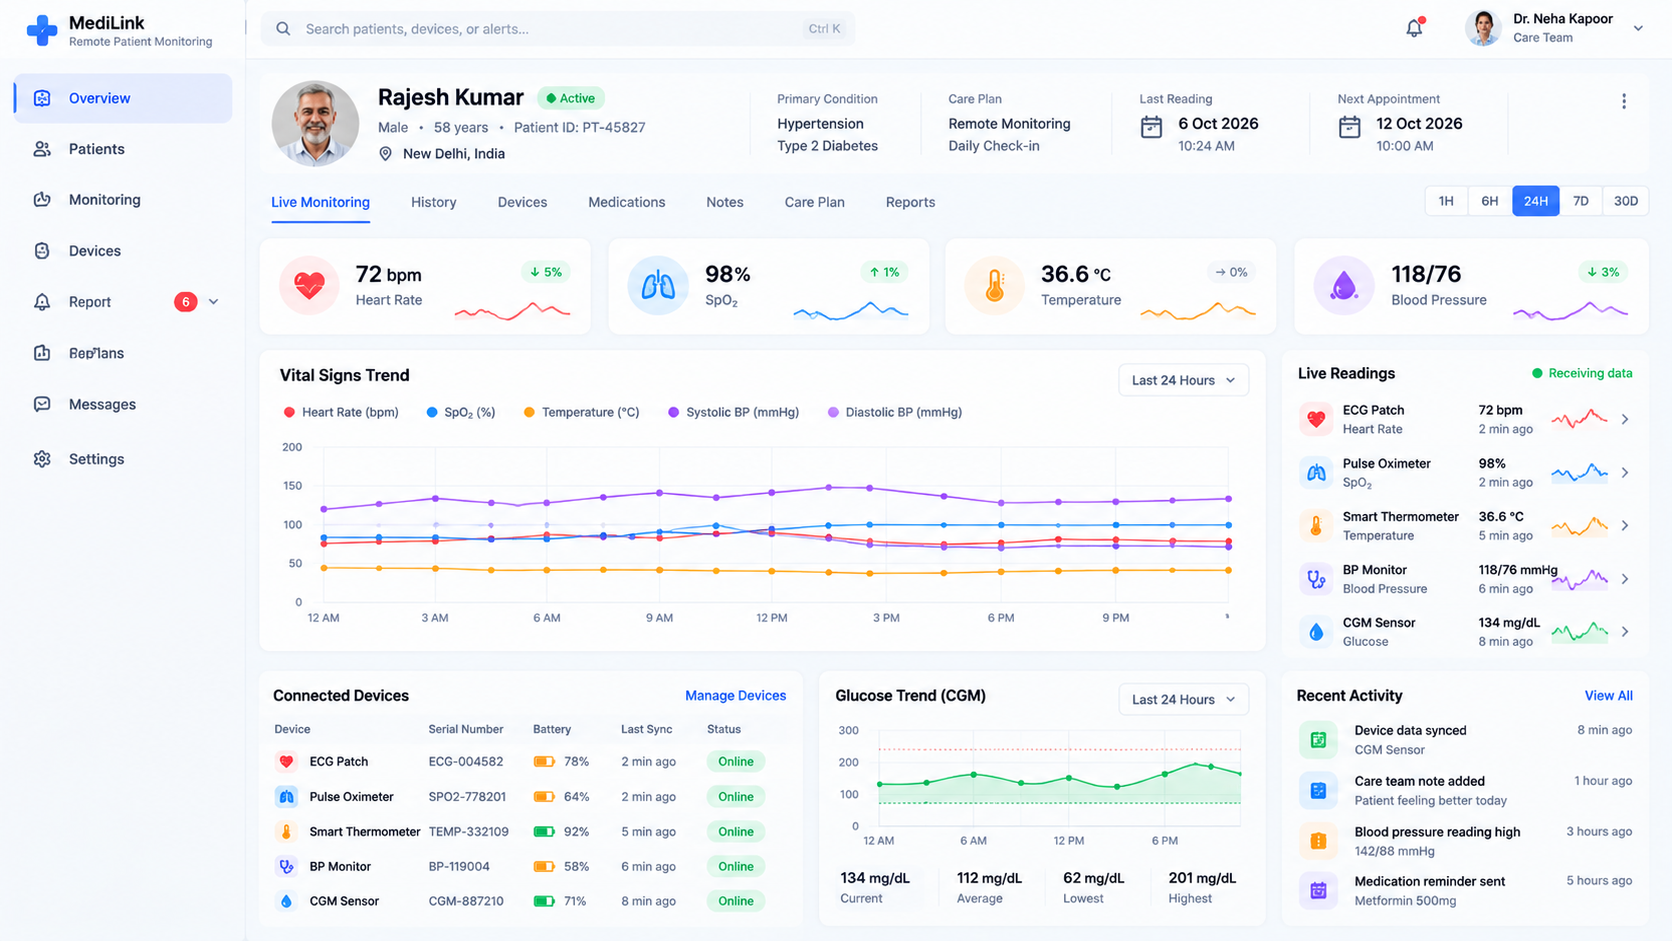

What this looks like in practice
Technology
Architecture
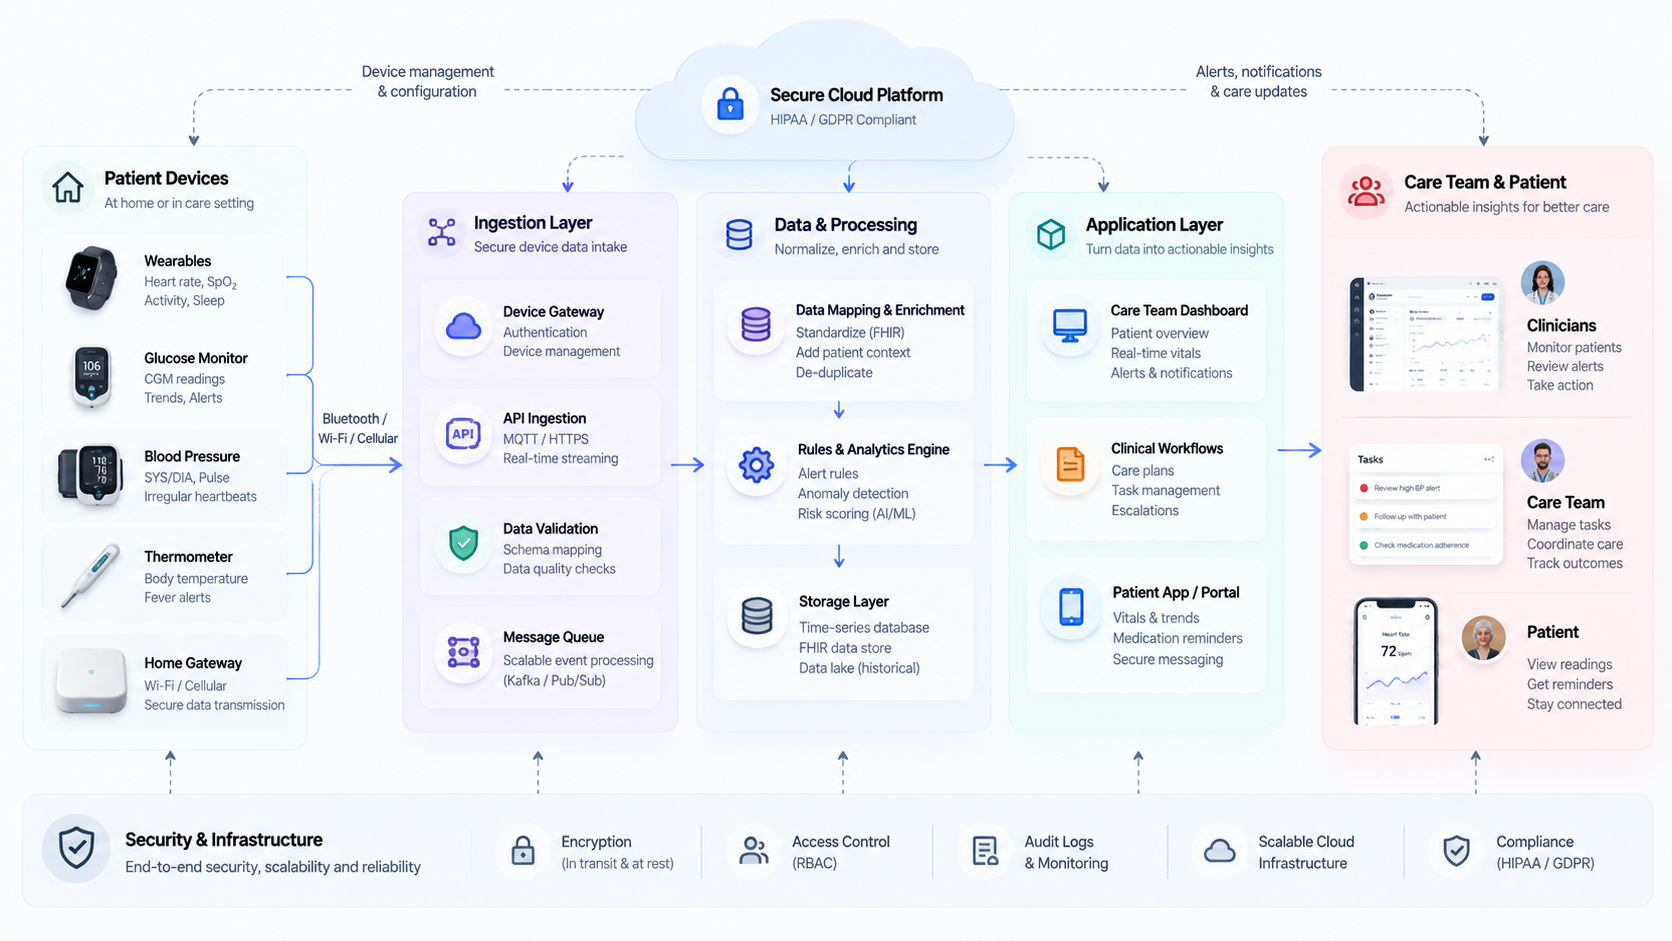
Expanded version of the diagram above
Frequently asked questions
Direct answers on hardware protocols, alert fatigue mitigation, closed device gateways, EHR records, and offline operation.
Everything around it. Typically the ingestion service, the mapping layer, storage, the rules that decide when something needs attention, the dashboards for each role, the fleet view for your operations team, and the integration into whichever clinical system the data needs to reach.
Often, through the manufacturer’s SDK or gateway. Where a device genuinely cannot be integrated, a gateway or an intermediate reader is sometimes the answer. We establish this during planning, because it changes the shape of the project.
By treating alerting as a clinical design question rather than a technical one. That means agreeing thresholds with the people who will respond, separating urgent from informational, using trends as well as single readings, and requiring acknowledgement so an unanswered alert escalates instead of disappearing.
It can, through FHIR or HL7, and usually should, so clinicians see it where they already work. What is written and how much of it is a clinical decision, since a continuous feed written in full will make a record unreadable.
The ingestion service accepts a backlog when a device reconnects, preserves the original timestamps rather than the arrival times, and raises a connectivity alert when a device has been silent longer than expected.
Talk to us about a connected care project
Bring the device, the setting it will be used in and the team who will act on the data. That is usually enough for a useful first conversation.